
Lasting Relief When Heartburn Won’t Quit
Some patients have daily heartburn, regurgitation or a nagging cough even with lifestyle changes and medication. At Matthew Lublin, MD, Dr. Lublin performs minimally invasive anti-reflux surgery that rebuilds the valve between the esophagus and stomach. This repair stops acid from backing up, so many patients can reduce or stop their reflux medications. Patients from Santa Monica, Encino, West Los Angeles and the San Fernando Valley are seen at either office.
Request an AppointmentUnderstanding GERD and Heartburn
People use the word “heartburn” for many kinds of digestive discomfort. Medically, it is a symptom of gastroesophageal reflux disease (GERD). In GERD, acidic stomach contents flow back up into the esophagus. This causes a harsh burning feeling behind the breastbone or just below the neck, and it can spread up through the chest into the throat. Many adults in the United States have heartburn at least once a month. For people with GERD, it happens often and is hard to control.
Heartburn is only one sign of reflux. Other common symptoms include:
- Regurgitation of sour fluid or food into the throat or mouth
- Difficulty swallowing or a sensation of food sticking
- Chronic cough, wheezing or hoarseness
- Sore throat or frequent throat clearing
- Nausea or vomiting
- Symptoms that worsen after meals or when lying down at night
Untreated reflux can do more than cause discomfort. Repeated acid exposure can inflame and scar the lower esophagus. Over time it can lead to narrowing (stricture) or Barrett’s esophagus, a change in the esophageal lining that needs monitoring.

What Causes GERD?
When you swallow, food moves down the esophagus, the tube that connects your mouth to your stomach. A small ring of muscle called the lower esophageal sphincter (LES) sits at the bottom of the esophagus. It works like a one-way valve. It opens to let food into the stomach, then closes tightly so acidic stomach juices stay where they belong.
GERD develops when the LES weakens or relaxes at the wrong times. Acid then washes back into the lower esophagus. The lining becomes irritated and inflamed, which causes heartburn and, over time, may damage the esophagus.
Risk Factors and the Hiatal Hernia Connection
Some people are born with a naturally weak sphincter. In others, reflux is triggered by fatty or spicy foods, certain medications, tight clothing, smoking, alcohol, vigorous exercise, or bending over and lying down. Excess body weight also adds pressure on the stomach and pushes acid upward.
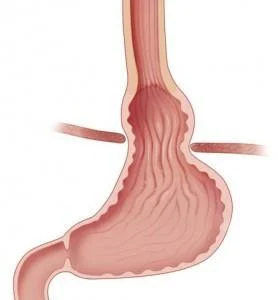
A hiatal hernia is a separate condition that is common in people with GERD. It happens when part of the stomach slides up through the diaphragm into the chest. This disrupts the normal barrier against reflux. Not every hiatal hernia causes heartburn, but when both are present, Dr. Lublin usually repairs the hernia during the same operation. Learn more on our hiatal hernia surgery page.
How GERD Is Treated
GERD treatment usually moves through three stages. Most patients start with the simplest options.
1. Lifestyle Changes
For many people, diet changes and over-the-counter antacids reduce how often symptoms happen and how severe they are. Other helpful steps include:
- Losing excess weight
- Quitting smoking and limiting alcohol
- Eating smaller meals and avoiding food two to three hours before bed
- Raising the head of the bed
2. Medication
If symptoms continue, medication is the next step. Antacids neutralize acid that is already in the stomach. Acid-reducing medications, including H2 blockers and proton pump inhibitors, lower the amount of acid the stomach makes. Prescription-strength versions can help heal an irritated esophagus. Medication controls acid, but it does not fix the faulty valve. Regurgitation and other symptoms may continue, and many patients need medication indefinitely.
3. Surgery
Surgery may be the right choice if you:
- Still have symptoms despite lifestyle changes and medication
- Want to avoid taking medication for the rest of your life
- Have side effects from reflux drugs
- Have complications from reflux, such as esophageal inflammation or a large hiatal hernia
Laparoscopic anti-reflux surgery is a highly effective, long-term treatment for GERD.
Laparoscopic Anti-Reflux Surgery
Laparoscopic anti-reflux surgery is commonly called a laparoscopic Nissen or Toupet fundoplication. It strengthens the valve between the esophagus and the stomach. The surgeon wraps the upper part of the stomach around the lowest part of the esophagus, much like a bun wraps around a hot dog. This creates a new, reliable barrier against reflux.
The procedure uses a few small incisions, a camera and fine instruments. Compared with open surgery, this usually means less pain, smaller scars and a faster recovery. For a closer look at the wrap techniques, see our page on fundoplication for GERD.
What to Expect From Surgery and Recovery
The operation usually takes about two hours and includes an overnight stay in the hospital. Most patients go home the next day.
Patients typically return to work about 3 to 7 days after surgery. The timing depends on comfort level and the type of work they do.
Your Post-Surgery Diet
Your diet advances in stages so the repair can heal:
- Clear liquids (about 3 to 5 days): broth, water, juice and flat soda.
- Soft diet (about 3 weeks): foods that are easy to chew and swallow. Examples include foods softened by cooking or mashing, canned or soft-cooked fruits and vegetables, and moist, tender meat, fish and poultry.
- Regular diet: resumed once soft foods are well tolerated.
It is common to feel full quickly or a little bloated after surgery. Some patients also have temporary difficulty swallowing (dysphagia). These symptoms usually improve within a few weeks.
Risks and Complications
As with any operation, laparoscopic anti-reflux surgery carries risks. Serious complications are uncommon and occur in fewer than 1% of cases. They include, but are not limited to:
- Pneumothorax (“dropped lung”)
- Perforation of the esophagus
- Bleeding
- Infection
Dr. Lublin will review your personal risk factors in detail during your consultation. Questions are welcome at either office by calling .
Anti-Reflux Surgery FAQs
Am I a candidate for laparoscopic anti-reflux surgery?
Good candidates have confirmed GERD that is not well controlled with lifestyle changes and medication. Others want to stop long-term medication, have side effects from reflux drugs, or have complications such as esophageal inflammation or a hiatal hernia. Testing helps confirm that surgery is the right choice.
What tests are done before GERD surgery?
Evaluation often includes an upper endoscopy and pH monitoring to measure acid exposure. Esophageal manometry checks how well the esophagus moves food, and imaging may be used to assess for a hiatal hernia. These results help Dr. Lublin choose the best type of wrap.
Will I be able to stop taking reflux medication?
Many patients can greatly reduce or stop acid-reducing medication after anti-reflux surgery. The operation fixes the faulty valve, while medication only reduces acid.
How long is the hospital stay?
The surgery takes about two hours, and most patients stay one night in the hospital and go home the next day.
When can I go back to work?
Most patients return to work within 3 to 7 days. The timing depends on comfort level and how physically demanding the job is.
Is trouble swallowing after surgery normal?
Yes, some temporary difficulty swallowing is common while swelling around the repair goes down. Following the staged liquid and soft diet helps, and this usually improves within a few weeks.
Can a hiatal hernia be repaired at the same time?
Yes. If a hiatal hernia is present, Dr. Lublin typically repairs it during the same laparoscopic procedure before creating the fundoplication.
Take the First Step Toward Life Without Reflux
If heartburn and regurgitation still control your days and nights despite medication, a consultation with Dr. Lublin can help you understand your options. Appointments are available at our Santa Monica and Encino offices. Call or request a visit online.