
Lasting Relief When Diverticulitis Keeps Coming Back
Many people manage diverticulitis with antibiotics and diet changes. Some have attacks that keep coming back, complications that don’t heal, or a severe infection that needs prompt care. Matthew Lublin, MD treats patients at offices in Santa Monica and Encino, CA. He uses laparoscopic and robotic colon surgery to remove the diseased section of colon through small incisions, which can help you recover sooner and get back to normal life.
Request an AppointmentDiverticulosis vs. Diverticulitis
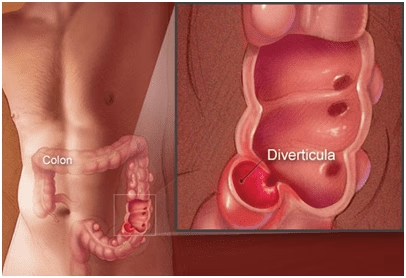
Diverticula are small pouches that bulge outward through weak spots in the wall of the colon. A single pouch is called a diverticulum. They most often form in the sigmoid colon, which is the lower left part of the large intestine, but they can develop anywhere along the colon.
Having these pouches is called diverticulosis. It is very common and becomes more likely with age. About 10 percent of Americans over 40 have it, and about half of Americans have it by age 60. Most people with diverticulosis never know it.
When one or more of the pouches becomes inflamed or infected, the condition is called diverticulitis. Only a minority of people with diverticulosis go on to develop it. Diverticulitis can range from a mild flare that settles down with treatment to a serious infection that needs surgery.

How an Infected Pouch Becomes a Serious Problem
When a pouch becomes inflamed, bacteria can pass through small tears in the bowel lining and form small abscesses. In some cases the infection spreads through the colon wall into the abdominal cavity.
This can cause swelling or rupture of the diverticula, larger abscesses, bowel blockage, or leakage through the bowel wall. These infections are serious and can be life-threatening without prompt treatment.
Causes and Risk Factors
The exact reason diverticula form is not fully understood, but a low-fiber diet is one of the most likely causes. Diverticular disease was first noticed in the United States in the early 1900s, around the time processed foods became a large part of the American diet and fiber intake dropped sharply.
The condition is common in industrialized countries such as the United States, England, and Australia, where low-fiber diets are typical. It is much less common in parts of Asia and Africa, where people tend to eat more fiber. Processed foods such as white bread, white rice, many breakfast cereals, crackers, and pretzels contain little fiber.


Why Fiber Matters for Colon Health
Fiber is the part of fruits, vegetables, and grains that the body cannot digest. Soluble fiber dissolves in water and becomes soft and gel-like in the intestines. Insoluble fiber passes through the intestines mostly unchanged. Both kinds keep stools soft and easy to pass.
Without enough fiber, constipation and hard stools are more likely. Straining raises the pressure inside the colon, and over time this pressure may push the lining out through weak spots and form pouches. Doctors are not certain why diverticula become inflamed. It may begin when stool or bacteria get trapped inside a pouch. An attack can start suddenly and without warning.
Symptoms of Diverticulitis
Most people with diverticulosis have no symptoms. Some notice bloating or cramping in the lower abdomen.
Diverticulitis symptoms are more severe. They often start suddenly but may also get worse over a few days. Common symptoms include:
- Abdominal pain, usually in the lower left side of the belly
- Tenderness when the lower left abdomen is pressed
- Fever and chills
- Nausea or vomiting
- Cramping
- Constipation or a change in bowel habits
How severe the symptoms are depends on how far the infection has spread and whether complications have developed.
How Diverticulitis Is Diagnosed
A CT scan of the abdomen is generally the best test to confirm diverticulitis. It shows inflammation, abscesses, and other complications. Diverticulosis without inflammation is usually found during a routine colonoscopy.
Treatment Options
Treatment depends on how severe your symptoms are. Most patients can be treated at home with oral antibiotics, a temporary change in diet, and sometimes stool softeners. Some patients need to be admitted to the hospital for IV antibiotics and closer monitoring. For many people, a high-fiber diet is the main long-term treatment.
Once diverticula form, they do not go away. Simple lifestyle changes, such as more fiber, plenty of fluids, and regular activity, can lower the chance of another attack.
When Surgery Is the Right Choice
Surgery is recommended when complications develop, when attacks keep coming back, or when severe attacks do not respond well to medication. The operation removes the diseased part of the colon, usually the sigmoid colon, and reconnects the healthy colon to the rectum.
Dr. Lublin performs diverticulitis surgery with minimally invasive laparoscopic and da Vinci robotic techniques whenever possible.
Immediate surgery may be needed for a perforation, a large abscess, peritonitis, complete bowel obstruction, or severe bleeding. In these emergencies, it is not always safe to rejoin the colon right away. The first operation cleans the infected abdomen, removes the damaged colon, and creates a temporary colostomy, an opening called a stoma, with stool collected in a pouch. A second operation several months later reconnects the colon and closes the stoma.


Complications of Diverticulitis
Diverticulitis can lead to bleeding, infection, small tears called perforations, abnormal connections called fistulas, or blockage of the colon. These complications always need treatment so they do not progress to serious illness.
Bleeding
Bleeding from diverticula is uncommon. It happens when a small blood vessel inside a pouch weakens and bursts, and blood may appear in the toilet or in the stool. Bleeding can be heavy, but it often stops on its own. Anyone with rectal bleeding, even a small amount, should see a doctor right away. Colonoscopy or angiography, an X-ray study using dye injected into an artery, can often find and stop the bleeding. If it continues, surgery to remove the bleeding section of colon may be needed.
Abscess, Perforation, and Peritonitis
Diverticulitis infections often clear up after a few days of antibiotics. If the infection worsens, an abscess, which is a pocket of pus, may form in or near the colon wall. Small abscesses may heal with antibiotics alone. Larger ones may need to be drained with a thin catheter placed through the skin, usually guided by a CT scan.
An infected pouch can also tear open and leak pus and stool into the abdominal cavity. This causes peritonitis. People with peritonitis are often very ill, with fever, nausea, vomiting, and severe abdominal tenderness. Peritonitis needs immediate surgery to clean the abdomen and remove the damaged colon. Without prompt treatment it can be fatal.
Fistula
A fistula is an abnormal connection between two organs, or between an organ and the skin. When infection spreads outside the colon, the inflamed colon can stick to nearby tissue and heal that way, forming a tunnel between them. The bladder, small intestine, and skin are most often involved.
The most common type connects the colon and the bladder. It affects men more often than women and can cause severe, long-lasting urinary tract infections. Surgery to remove the fistula and the affected part of the colon corrects the problem.
Intestinal Obstruction
Repeated infection can leave scar tissue that partly or completely blocks the intestine, so bowel contents cannot move through normally. A complete blockage needs emergency surgery. A partial blockage is not an emergency, so surgery can be planned ahead of time.
The Advantages of Laparoscopic Colon Resection
Minimally invasive laparoscopic colon resection lets Dr. Lublin perform many common colon procedures through a few small incisions instead of one long abdominal cut. Compared with open surgery, patients often have less pain, smaller scars, and a shorter hospital stay. Many go home within a few days and return to normal activities sooner. Dr. Lublin sees patients in both Santa Monica and Encino to review your history, imaging, and treatment options.
Diverticulitis Surgery FAQs
How do I know if I need surgery for diverticulitis?
Surgery is usually recommended when attacks keep coming back, when symptoms don’t improve with antibiotics, or when complications such as an abscess, fistula, bowel blockage, perforation, or heavy bleeding develop. Dr. Lublin reviews your history and CT scans to decide whether surgery is the right step for you.
What part of the colon is removed?
In most cases, the sigmoid colon, the lower left portion of the large intestine where diverticulitis usually occurs, is removed. The healthy colon is then reconnected to the rectum so bowel function can continue normally.
Can diverticulitis surgery be done laparoscopically?
Yes. Many diverticulitis operations can be done with laparoscopic or robotic techniques through several small incisions. This approach often means less pain, smaller scars, a shorter hospital stay, and a faster return to daily activities than open surgery.
Will I need a colostomy bag?
Most planned diverticulitis operations do not need a colostomy. A temporary colostomy is more likely after emergency surgery for perforation, peritonitis, or severe infection, when it isn’t safe to reconnect the colon right away. In those cases the colon is usually reconnected in a second operation several months later.
How long is recovery after diverticulitis surgery?
After minimally invasive surgery, many patients go home within a few days. Most return to light activity within a couple of weeks. Full recovery varies with your health and whether the surgery was planned or done on an emergency basis.
Can diverticulitis come back after surgery?
Removing the diseased section of colon greatly lowers the chance of another attack, because that section is where most attacks occur. Pouches may still exist elsewhere in the colon, so a high-fiber diet and healthy habits are still recommended after surgery.
Where can I see Dr. Lublin for diverticulitis care?
Dr. Lublin sees patients at his offices in Santa Monica and Encino, CA. Call (310) 828-2212 to schedule a consultation at whichever location is more convenient for you.